DSIP is a chain of nine amino acids, first found in rabbit blood in 1977 during deep sleep. Small human studies from the 1970s and 1980s tested it for insomnia and drug withdrawal. Its role in sleep is still disputed.
In brief
- Monnier and Schoenenberger first pulled it from rabbit brain blood in 1977 during electrically triggered deep sleep, making it one of the earliest peptides proposed as a sleep signal and still a reference point when sleep peptides are compared.
- Early animal and human studies tested whether it shapes deep, slow-wave sleep, but later results did not agree and no receptor of its own has been confirmed, so how it works is still unclear.
- It has also been tested for effects on the stress hormones ACTH and cortisol, on long-term pain and opioid withdrawal, and in animals for antioxidant and stress-resistance effects.
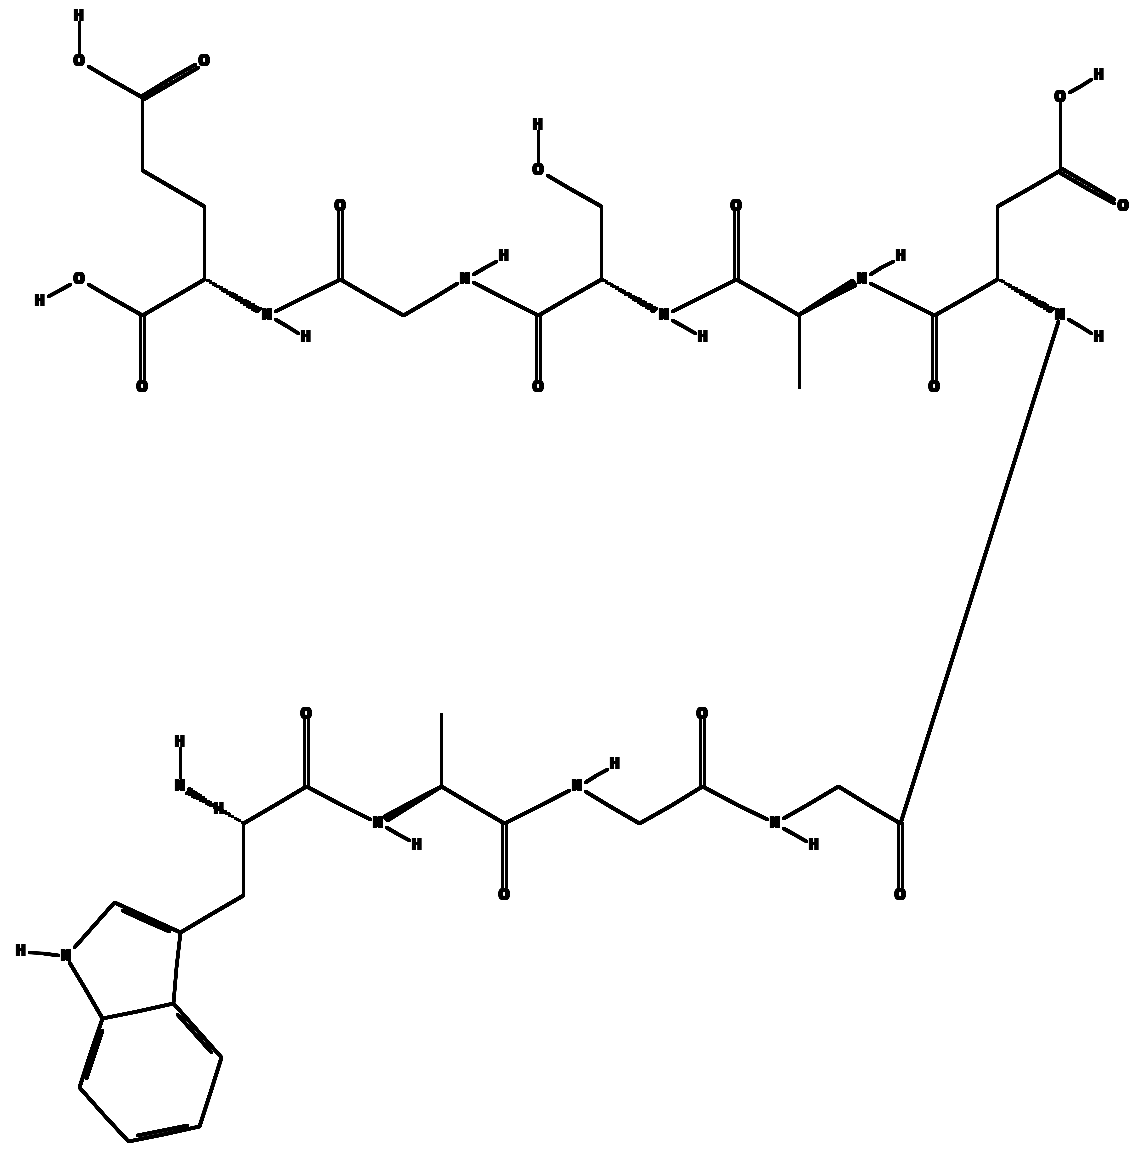
What DSIP is
DSIP is a lab-made peptide that has been tested in a handful of small human studies, plus animals and cells. Most of the human work dates from the late 1970s to the late 1980s. The patients had long-term insomnia, or were coming off opiates or alcohol [3], [5], [8], [9], [13]. Some trials were open-label, which means everyone knew who got the compound. Others compared it with a placebo, but only for a short time.
As of 2026, this guide rates the evidence as early clinical. No trial that meets a modern Phase 2 or Phase 3 standard turned up in the papers reviewed. DSIP is not approved as a medicine for people in any country.
A peptide is a short chain of amino acids, the building blocks of protein. DSIP has nine of them: Trp-Ala-Gly-Gly-Asp-Ala-Ser-Gly-Glu (WAGGDASGE). The letters stand for delta sleep-inducing peptide. Delta waves are the slow brain waves of deep sleep.
Where it came from
The story starts with rabbits. In older experiments, blood from a donor rabbit in a sleep state was passed into a second animal. The second animal’s brain waves, read by EEG, were reported to change. Scientists went looking for whatever in the blood caused that.
In 1977, Schoenenberger and Monnier pulled DSIP out of blood draining from rabbit brains. They took the blood while the rabbits were in delta-wave sleep brought on by electrical stimulation. They put DSIP forward as a candidate for the sleep factor [1]. A second paper came out the next year. It gave the amino acid order, described how to make the peptide chemically, and confirmed that the lab-made copy promoted delta waves the way the natural extract had [2].
A name that outlived its finding
Since then, DSIP has shown up in a large but scattered set of papers. They cover sleep, hormones controlled by the brain, pain, withdrawal, and aging studies in animals [6], [7], [11].
The name may have lasted longer than the result behind it. Later work could not reliably confirm that DSIP is a natural sleep factor carried in blood. Whether it has any real part in the sleep and wake cycle is still argued over [19].
This guide sums up the peer-reviewed research on DSIP for education and lab research. For laboratory research use only. Not for human consumption.
How much research there is
A few small, old human studies, some animal work that is still going, and no modern trial.
| Question | Answer |
|---|---|
| Stage of evidence | Early clinical. Small human studies from the late 1970s to late 1980s, either open-label or placebo-controlled for a short course. Animal work on antioxidant, stress and memory effects continues. No modern Phase 2 or Phase 3 trial was found |
| Kinds of studies | Small human trials on sleep and withdrawal, some with placebo and some open-label. Animal and cell studies on binding sites and pain. Rodent studies on antioxidant effects and lifespan |
| Who or what was tested | Adults with long-term insomnia. Adults in opiate withdrawal, alcohol withdrawal or both. Healthy volunteers in hormone studies. Rodents and cultured cells. No data on children and no long-term human follow-up were found |
| Checked by other labs | Not much. The sleep and withdrawal results come mostly from a few overlapping European groups working in the late 1970s and 1980s [3], [5], [8], [9], [13]. The antioxidant and lifespan results come mostly from a separate research tradition [17], [18]. The two bodies of work have rarely tested each other’s findings |
| Where the work comes from | Most of the human papers found for this guide come from a few European teams, all active within a fairly narrow span of years |
| Longest study | Seven nights of dosing in the one double-blind, placebo-controlled trial found [13]. Some open studies checked patients three to seven months after treatment [9], but with very little blinding or control |
| Regulators | A research compound under study. No approval from the FDA, the EMA or the MHRA was found for any use |
| Do the results agree | Partly. Better sleep and easier withdrawal are reported fairly steadily, but only within the small overlapping teams that ran those studies. Human results on the stress hormone ACTH directly conflict [15], [16]. A 2006 review found that the claim that DSIP is a natural sleep factor is still unsettled [19] |
How it might work
Nobody knows for sure. DSIP has no agreed receptor of its own, meaning no confirmed place in the body where it attaches. The papers on how it acts are patchy, and some flatly disagree. A widely cited 2006 review called the biology behind the peptide “a still unresolved riddle” [19].
What follows is a list of competing ideas. None of them is a proven way that DSIP works.
The hunt for a receptor
In the early 1980s, scientists tagged DSIP with a radioactive label ([3H]DSIP) and added it to rat brainstem nerve cells grown in a dish. The tagged peptide stuck to specific sites, and those sites could be filled up. They were clustered in cell groups tied to sleep and to automatic body functions [4]. At the time, this looked like an early sign of a DSIP receptor.
More than forty years later, nobody has cloned that receptor or worked out its molecular makeup. No confirmed DSIP receptor exists in the papers reviewed here [19]. So researchers have suggested that DSIP may act, at least partly, in an indirect way, by changing how other known brain and hormone systems behave.
GABA and glutamate
GABA is the brain’s main calming chemical. Glutamate is its main exciting one. Several lines of work suggest that DSIP shifts both signals in the brainstem and thalamus circuits that control sleep. On this view, its reported effects on EEG state and on the pattern of sleep stages come from that shift, not from a receptor of its own [7], [11].
The idea fits a wider problem. Scientists have struggled to tie the reported effects of DSIP on behavior and brain activity to one clear molecular target. Nobody has turned this idea into a specific, confirmed signaling route.
Stress hormones and opioids
Other work looks at the HPA axis. That is the chain from the hypothalamus in the brain to the pituitary gland to the adrenal glands, and it runs the stress response.
- In animals. CRF is a brain signal that normally makes the adrenal glands release the stress hormone corticosterone. DSIP given into a vein lowered that release. The authors took this as a sign that DSIP puts a brake on the system at the pituitary or above it [10].
- In healthy volunteers. One study found less ACTH in blood plasma after DSIP was injected into a vein. ACTH is the pituitary hormone that tells the adrenal glands to act [15].
- In a later human study. A team using different methods found that DSIP made no significant difference to ACTH or cortisol released in response to CRH or a meal. The authors said themselves that this clashed with the earlier report [16].
Pain research adds an opioid angle. In animals, DSIP given directly into the central nervous system raised the pain threshold. The authors proposed that it works partly by spurring the body’s own opioid signals, not by attaching to opioid receptors itself [14].
It breaks down fast
One practical theme keeps coming up. DSIP does not last long in body fluids. A study of DSIP and two close relatives in plasma and serum found that enzymes broke them down quickly. The peptides also tended to clump together. Both facts make dosing studies hard to read and blur the picture of how the body handles the compound [12].
This fast turnover has been raised many times as a limit on the research. After a dose into the body, any proposed action has only a short window in which to happen. It is also one of several reasons researchers give for why DSIP effects have been hard to repeat from study to study and lab to lab [19].
What the studies found
The findings fall into four areas that are only loosely linked: sleep and brain waves, stress hormones, pain and withdrawal, and antioxidant and lifespan work in animals.
Sleep and brain waves
- Disturbed sleep, early human study. Patients given DSIP into a vein said they slept better, and their pattern of sleep stages moved back toward normal over repeated doses. The authors noted that the effect seemed to build with each injection [3].
- Severe insomnia, open study. After a course of ten injections, sleep returned to normal in the authors’ own judgment. Only a few patients were studied. In most of them the gain was said to hold at checkups three to seven months later [9].
- Long-term insomnia, double-blind trial. Middle-aged patients got DSIP or a placebo for seven nights. Those on DSIP slept more efficiently at night and were more alert by day. Some of the benefit was reported to carry into the first night after treatment ended [13].
- Thin air, rodent study. Newer animal work tested a version of DSIP with a phosphate group added. Rodents were kept in low oxygen like that found at high altitude. Their sleep pattern improved, they did better on a spatial memory task, and they made more p-CREB, a signaling protein linked to memory. This shows DSIP research did not stop with the sleep papers of the 1970s and 1980s [20].
Even so, few outside labs have repeated the sleep effect. A thorough review found no convincing proof that DSIP is a natural controller of slow-wave sleep in people [19].
Stress hormones
- Animals: DSIP into a vein cut the corticosterone release that CRF sets off. The authors read this as a braking action on the HPA axis at or near the pituitary [10].
- Healthy volunteers: ACTH in plasma stayed lower for at least three hours after a DSIP injection into a vein [15].
- A later human study with a different design: DSIP had no significant effect on ACTH or cortisol released after CRH or a meal. The authors pointed out that this did not match what the animal studies led them to expect [16].
Put together, the human stress hormone studies truly disagree with one another. They do not show a confirmed, repeatable effect on the HPA axis.
Pain and withdrawal
- Pain in animals: DSIP given into the central nervous system had a strong pain-dulling effect. The authors thought it acted indirectly, by raising the body’s own opioid signals, and not by binding to opioid receptors [14].
- Opiate withdrawal: patients with withdrawal symptoms got DSIP into a vein. Most of the opiate-dependent patients who could be assessed improved. Relief of physical symptoms seemed to come on fast [5].
- Alcohol and opiate withdrawal: a larger follow-up study added patients withdrawing from alcohol. For both substances, the signs and symptoms went away or got much better in most patients [8].
These withdrawal studies were small. They had little or no control group, and they came from a small circle of researchers whose teams overlapped. They are best read as early, exploratory reports from the clinic, not as proof that DSIP works.
Antioxidant effects and lifespan in animals
- Cold stress in rats: DSIP changed free radical activity in rats under cold stress. It shifted markers of lipid peroxidation, which is free radical damage to fats, and it changed how active antioxidant enzymes were. The authors proposed a protective, antioxidant-type action against stress [17].
- Lifespan: a long-term rodent study tested Deltaran, a preparation that contains DSIP. It tracked signs of aging, total lifespan and tumors that arose on their own in female mice. The treated group did better on some signs of aging and on lifespan measures [18].
Most of this work comes from a few groups that share one research tradition. In the papers reviewed for this guide, no lab outside that tradition has repeated it.
Safety
What the studies reported
- In people. The small insomnia studies [3], [9], [13] and the opiate and alcohol withdrawal studies [5], [8] reported no serious side effects tied to treatment. These are old studies, though. By modern standards, they did not track side effects in a thorough, organized way.
- In rodents. The antioxidant and lifespan studies reported no new signs of toxicity from DSIP or from the DSIP preparation they used [17], [18].
- Short exposure. DSIP is reported to break down quickly in plasma [12]. Researchers have suggested the body may therefore be exposed to it only briefly after a typical dose, which could limit the room for lasting side effects. That is a proposed line of reasoning. It has not been formally measured as a safety property.
What is not known
- No modern trial has confirmed the older results. The human studies are small and old, and several had very little control.
- No long-term human safety data were found. Dosing courses ran for a small number of days to weeks at most.
- No formal drug interaction studies were found.
- The receptor and the way DSIP works are still unconfirmed [19]. Without a clearly defined target, nobody can judge whether the safety picture is complete.
Legal status in the US
- Not approved. As of 2026, DSIP is a research compound under study. No approval from the FDA, the EMA in Europe or the MHRA in the UK was found for any use, and it is not approved as a human medicine anywhere in the world.
- Sport. DSIP is not listed by name on the current World Anti-Doping Agency Prohibited List. Because it is a peptide, it would be expected to fall, if it applied at all, under class S2. That class covers peptide hormones, growth factors, related substances and mimetics.
- Research use. It is supplied strictly for laboratory research use only, not for human or competitive use.
Limits of the research
- Small, old studies. Most of the human studies date from the late 1970s and the 1980s. They enrolled few people, and several were open-label or barely controlled [3], [5], [8], [9].
- No modern trial to confirm them. Nothing that counts as a Phase 2 or Phase 3 trial by current regulatory standards has been found. The placebo-controlled human evidence that exists covers short dosing courses only [13].
- Results that conflict or do not repeat. Different research groups got directly opposing results on stress hormones in people [15], [16]. The claim that DSIP is a sleep factor carried in blood has not held up reliably across the wider body of papers [19].
- Four separate fields. Sleep, withdrawal, stress hormones, and antioxidant and lifespan work are separate lines of research. Mostly different groups ran them. A finding in one field cannot be carried over to another.
- No known way of working. No DSIP receptor has been confirmed. The proposed routes through GABA, glutamate, opioids and brain-controlled hormones are partial and unproven. Fast breakdown in plasma makes dosing studies harder to read [4], [7], [11], [12], [14], [19].
- A few research groups. Much of the human work comes from a few overlapping European teams active over a short span of years. Much of the animal antioxidant and lifespan work comes from a separate tradition that is just as narrow [17], [18]. In both cases, few outside labs have cross-checked the results.
- Possible missing results. Bias in what got published and reported cannot be ruled out. Much of this research is old, and reporting standards were looser when most of it was done.
Nearly 50 years after DSIP was found, small old studies hint at effects on sleep and withdrawal, but no modern trial has confirmed them and nobody has shown how it works.
References
Selected peer-reviewed references, each verified against the CrossRef API before inclusion. Ordered by date of publication.
- Schoenenberger GA, Monnier M (1977). Characterization of a delta-electroencephalogram (-sleep)-inducing peptide. Proceedings of the National Academy of Sciences, 74(3), 1282–1286. DOI: 10.1073/pnas.74.3.1282
- Schoenenberger GA, Maier PF, Tobler HJ, Wilson K, Monnier M (1978). The delta EEG (sleep)-inducing peptide (DSIP). XI. Amino-acid analysis, sequence, synthesis and activity of the nonapeptide. Pflugers Archiv: European Journal of Physiology, 376(2), 119–129. DOI: 10.1007/BF00581575
- Schneider-Helmert D, Schoenenberger GA (1981). The influence of synthetic DSIP (delta-sleep-inducing-peptide) on disturbed human sleep. Experientia, 37(9), 913–917. DOI: 10.1007/BF01971753
- Hösli E, Schoenenberger GA, Hösli L (1983). Autoradiographic localization of binding sites for the delta sleep-inducing peptide ([3H]DSIP) on neurons of cultured rat brainstem. Brain Research, 279(1–2), 374–376. DOI: 10.1016/0006-8993(83)90213-5
- Dick P, Grandjean ME, Tissot R (1983). Successful treatment of withdrawal symptoms with delta sleep-inducing peptide, a neuropeptide with potential agonistic activity on opiate receptors. Neuropsychobiology, 10(4), 205–208. DOI: 10.1159/000118012
- Schoenenberger GA (1984). Characterization, properties and multivariate functions of delta-sleep-inducing peptide (DSIP). European Neurology, 23(5), 321–345. DOI: 10.1159/000115711
- Graf MV, Kastin AJ (1984). Delta-sleep-inducing peptide (DSIP): a review. Neuroscience & Biobehavioral Reviews, 8(1), 83–93. DOI: 10.1016/0149-7634(84)90022-8
- Dick P, Costa C, Fayolle K, Grandjean ME, Khoshbeen A, Tissot R (1984). DSIP in the treatment of withdrawal syndromes from alcohol and opiates. European Neurology, 23(5), 364–371. DOI: 10.1159/000115715
- Schneider-Helmert D (1984). DSIP in insomnia. European Neurology, 23(5), 358–363. DOI: 10.1159/000115714
- Graf MV, Kastin AJ, Coy DH, Fischman AJ (1985). Delta-sleep-inducing peptide reduces CRF-induced corticosterone release. Neuroendocrinology, 41(4), 353–356. DOI: 10.1159/000124200
- Graf MV, Kastin AJ (1986). Delta-sleep-inducing peptide (DSIP): an update. Peptides, 7(6), 1165–1187. DOI: 10.1016/0196-9781(86)90148-8
- Graf MV, Saegesser B, Schoenenberger GA (1987). Degradation and aggregation of delta sleep-inducing peptide (DSIP) and two analogs in plasma and serum. Peptides, 8(4), 599–603. DOI: 10.1016/0196-9781(87)90031-3
- Schneider-Helmert D (1987). Effects of delta-sleep-inducing peptide on 24-hour sleep-wake behaviour in severe chronic insomnia. European Neurology, 27(2), 120–129. DOI: 10.1159/000116143
- Nakamura A, Nakashima M, Sugao T, Kanemoto H, Fukumura Y, Shiomi H (1988). Potent antinociceptive effect of centrally administered delta-sleep-inducing peptide (DSIP). European Journal of Pharmacology, 155(3), 247–253. DOI: 10.1016/0014-2999(88)90510-9
- Bjartell A, Ekman R, Bergquist S, Widerlöv E (1989). Reduction of immunoreactive ACTH in plasma following intravenous injection of delta sleep-inducing peptide in man. Psychoneuroendocrinology, 14(5), 347–355. DOI: 10.1016/0306-4530(89)90004-8
- Späth-Schwalbe E, Schäfer A, Uthgenannt D, Born J, Fehm HL (1995). Delta-sleep-inducing peptide does not affect CRH and meal-induced ACTH and cortisol secretion. Psychoneuroendocrinology, 20(3), 231–237. DOI: 10.1016/0306-4530(94)00050-k
- Shustanova TA, Bondarenko TI, Milyutina NP, Mikhaleva II (2001). Regulation of free radical processes by delta-sleep inducing peptide in rat tissues under cold stress. Biochemistry (Moscow), 66(6), 632–639. DOI: 10.1023/a:1010255230338
- Popovich IG, Voitenkov BO, Anisimov VN, Ivanov VT, et al. (2003). Effect of delta-sleep inducing peptide-containing preparation Deltaran on biomarkers of aging, life span and spontaneous tumor incidence in female SHR mice. Mechanisms of Ageing and Development, 124(6), 721–731. DOI: 10.1016/s0047-6374(03)00082-4
- Kovalzon VM, Strekalova TV (2006). Delta sleep-inducing peptide (DSIP): a still unresolved riddle. Journal of Neurochemistry, 97(2), 303–309. DOI: 10.1111/j.1471-4159.2006.03693.x
- Roy K, Chauhan G, Kumari P, Wadhwa M, et al. (2018). Phosphorylated delta sleep inducing peptide restores spatial memory and p-CREB expression by improving sleep architecture at high altitude. Life Sciences, 209, 282–290. DOI: 10.1016/j.lfs.2018.08.026