Glutathione is a small molecule made of three amino acids. Cells make it and use it as their main antioxidant. Its chemistry is well mapped, but human trials of glutathione supplements are small and their results are mixed.
In brief
- It is the main antioxidant inside cells. The glutathione peroxidase (GSH-Px) enzymes cannot work without it, and it is at the center of a cell's redox balance.
- Plain GSH taken by mouth is poorly absorbed. Scientists have tested IV, liposomal and under-the-tongue forms as other ways to deliver it.
- Its role as an antioxidant and enzyme helper is well established. Wider supplement claims, such as skin lightening, are still being tested and are not settled in peer-reviewed research.
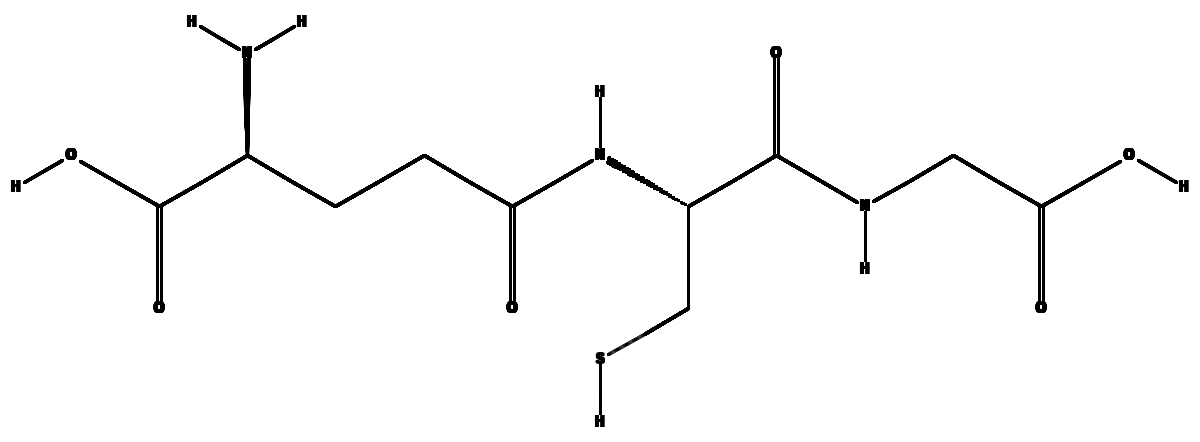
What Glutathione is
Glutathione is a small molecule that cells make to protect themselves from reactive chemicals. Scientists have mapped its chemistry in detail over decades. The proof that taking it as a supplement helps people is much weaker. That proof rests on a small number of human trials, most with fewer than 100 people. As of April 2026, the FDA, the MHRA and the EMA have not approved it as a treatment. The one exception is a set of specific IV products used in a few places for defined conditions.
Glutathione is often shortened to GSH. It is a tripeptide, which means three amino acids joined in a chain. The three are glutamate, cysteine and glycine. The full chemical name is γ-L-glutamyl-L-cysteinyl-glycine, and it weighs 307 Da.
One of its links is unusual. Proteins join amino acids with a standard α-peptide bond. In GSH, the side chain of glutamate is tied to cysteine with a γ-peptide bond. Most peptidases, the enzymes that cut peptides, cannot break it. This helps explain why GSH is so stable inside cells [1].
No other non-enzyme antioxidant is as plentiful inside the cells of mammals. Levels in a cell usually run from 1 to 10 mM. That is orders of magnitude above the level in blood plasma.
GSH has two forms, and each can turn into the other [4], [7]:
- GSH, the reduced form. This is the active antioxidant.
- GSSG, the oxidized form. Two GSH molecules give up electrons to disarm reactive chemicals. They then join as a pair.
Scientists often use the ratio of GSH to GSSG as a marker of a cell’s redox state, its balance between oxidants and antioxidants.
Cells build GSH from scratch in two steps. Each step uses ATP, the cell’s energy molecule. An enzyme called γ-glutamylcysteine synthetase (γ-GCS) runs the first step and sets the pace. Glutathione synthetase (GSS) runs the second. The supply of cysteine is the main limit. That is why compounds that deliver cysteine, such as NAC (N-acetylcysteine), are able to lift GSH in cells by an indirect route [7].
One split runs through all of the research. The biochemistry is very well described. For raising GSH with supplements, the clinical evidence is far more mixed. Little of a swallowed dose gets absorbed, because the gut breaks most of it down. Doses into a vein (IV) or a muscle (IM) have only been tested in small clinical settings, often with no control group [2], [10].
How much research there is
The evidence is truly mixed. Few topics in cell biology are as well mapped as this chemistry. The supplement trials are far weaker, and the two should not be confused.
| Question | Answer |
|---|---|
| The basic chemistry | Strong. Decades of core work. How it is made, how it cycles, and what it does for enzymes are well mapped |
| Plain GSH by mouth | Poor absorption. Witschi 1992 saw no rise in plasma after one 3 g dose. The gut breaks most of it down |
| Liposomal, under-the-tongue or long-term oral GSH | Early. Rises in biomarkers in three small studies (Schmitt 2015, Richie 2015, Sinha 2018) |
| IV or IM dosing | Limited. A few small trials, in Parkinson’s and NAFLD. No product is approved by the FDA or MHRA for those uses |
| Randomized trials in Parkinson’s disease | Mixed. At the dose it tested, the Hauser 2009 trial saw no significant benefit. Open-label work before it was positive, with no controls |
| Skin lightening | Disputed. Sonthalia’s two systematic reviews (2016, 2018) call the evidence insufficient. Regulators have warned about injections |
| Randomized controlled trials overall | Few. Usually under 100 people. Most measure biomarkers, not clinical results |
| The NAC comparison | NAC supplies cysteine and raises GSH in cells by a well-described route. It is FDA and MHRA approved for specific conditions |
Nobody questions that GSH matters a great deal as a molecule. Two things are still open. One is whether GSH given from outside, by any route, changes the course of disease in humans in a meaningful way. The other is which delivery forms, if any, raise tissue levels enough to bring a clinical benefit.
How it works
Glutathione takes part in dozens of chemical pathways. Three roles matter most for the research: direct antioxidant chemistry, helping detox enzymes, and cell signaling.
As an antioxidant
The working part of GSH is a thiol group (-SH) on its cysteine. The thiol gives up electrons easily. That lets GSH directly disarm reactive oxygen species (ROS) and reactive nitrogen species (RNS). Examples are singlet oxygen, peroxynitrite and hydroxyl radicals [7].
The cycle runs like this:
- A GSH molecule gives away an electron and becomes a thiyl radical (GS•).
- Two GS• radicals quickly pair up. The pair is GSSG, held by a disulfide bond.
- An enzyme, glutathione reductase (GR), turns GSSG back into 2×GSH. It takes the electrons from NADPH.
In a healthy cell, the cytosol (the fluid inside) holds more than 100 GSH for each GSSG. A drop in that ratio is called oxidative stress. It goes along with many disease states, such as chronic inflammation, loss of nerve cells, insulin resistance and poor liver function [6].
Meister and colleagues described this cycle in full in the 1980s. Their work is still the reference for the field [1].
As a helper for detox enzymes
GSH does more than mop up radicals. Two enzyme families do most of a cell’s detox work, and neither can run without GSH as a cofactor, a required helper molecule.
- Glutathione peroxidases (GSH-Px or GPx). These enzymes need selenium. They turn hydrogen peroxide (H2O2) into water, and lipid hydroperoxides into lipid alcohols. Each round uses up two GSH molecules. GPx is one of the main brakes on lipid peroxidation, which is oxidant damage to the fats in cell membranes.
- Glutathione S-transferases (GSTs). This is a big family of phase II detox enzymes. They attach GSH to electrophilic xenobiotics (reactive foreign chemicals), to drug breakdown products, and to reactive aldehydes the body makes, such as 4-hydroxynonenal. The cell ships the tagged molecules out. They leave the body in urine as mercapturic acids.
Together these two families handle much of the load from the cell’s own oxidant waste and from outside chemicals. When GSH runs low, both lines of defense weaken at once. That is the core reason doctors are interested in GSH levels as a target for treatment [6], [7].
As a signal
Newer research treats GSH as more than a bulk buffer. It also takes an active part in cell signaling.
GSH can attach to cysteine units on proteins and come off again. The process is called S-glutathionylation, and it forms a mixed disulfide written protein-SSG. This change happens after a protein is built. It alters how ion channels, enzymes and transcription factors behave. More and more, scientists see it as a signal that responds to redox state, much as phosphorylation works as a signal [7].
GSH levels affect several key signaling hubs:
- the Nrf2/Keap1 antioxidant response pathway
- NF-κB inflammatory signaling
- control of apoptosis, or planned cell death, through thiols on caspase enzymes
- the mitochondrial permeability transition
Disturbed GSH balance has been tied to the progress of five conditions: cancer, diabetes, HIV, cardiovascular disease and neurodegeneration. In most of these, it is still argued whether low GSH is a cause or a result [6], [14].
The older picture was an “antioxidant reservoir.” The newer one is a “redox signaling currency.” The change matters for how supplement plans get designed and judged.
What the studies found
Glutathione research runs from basic chemistry to small clinical trials. There is also a large gray literature of supplement claims. The five areas that follow are the ones cited most. The strength of the evidence differs a lot from one to the next.
Taken by mouth
The key question is simple. Does swallowed GSH raise GSH inside the tissues that matter?
Witschi and colleagues ran the first controlled human study on this in 1992. Healthy volunteers swallowed a 3 g dose of GSH, and the team measured their plasma. GSH, GSSG and cysteine in plasma did not rise by a significant amount. The authors called oral GSH “not a reliable means of increasing circulating glutathione concentrations” [2]. Several later studies found the same. It is still the working assumption for plain oral GSH.
Since 2015, scientists have tested whether new delivery forms can get past the gut.
- Richie and colleagues, 2015. This randomized controlled trial lasted six months and had 54 people. Each day they took oral GSH, at 250 mg or at 1,000 mg, or a placebo. GSH rose in whole blood, red blood cells, plasma and cheek cells, and it rose more at the higher dose. Natural killer cells, a kind of immune cell, also killed targets slightly better at the higher dose [9]. Few trials in humans, large or small, have run this long. It gave cautious support to steady oral use.
- Schmitt and colleagues, 2015. This crossover study compared three things: NAC, standard GSH by mouth, and a new form held under the tongue. In a crossover study, each person tries every treatment in turn. At the same dose, the under-the-tongue form improved markers of oxidative stress more than swallowed GSH did. That backs the idea that getting around gut breakdown matters [10].
- Sinha and colleagues, 2018. This crossover trial tested liposomal GSH, which is GSH packed in tiny fat bubbles. Healthy adults took 500 or 1,000 mg a day for one to four weeks. Blood stores of GSH went up, and so did markers of immune function. It is an early sign that liposomal delivery may work [13].
These results call for caution. The samples are small. Most outcomes are biomarkers, not clinical results. And the field lacks direct comparisons with cysteine donors like NAC. Those are mostly cheaper and better understood.
Given by IV
IV and IM doses skip the gut completely. Doctors have used them in a few small clinical settings, mainly in Japan and in some of mainland Europe. The evidence runs from open-label case series, where everyone knows what was given, to small randomized controlled trials.
Parkinson’s disease is the most studied use of IV GSH, and it has its own section below. IV GSH has also been tested in three other conditions:
- non-alcoholic fatty liver disease [12]
- peripheral neuropathy (nerve damage in the limbs) caused by chemotherapy
- peripheral arterial disease
Taken together, the evidence for these is thin. No GSH product for IV use has marketing approval from the FDA or the MHRA for any of them. In the United States, the FDA issued a warning in 2019 about compounded IV GSH. It concerned sterility and how the products were compounded.
Smaller studies have used IM doses, usually 600 mg a day or more. Those studies report higher plasma GSH. Data that link plasma levels to what reaches tissue are still limited.
Fatty liver
The liver makes most of the body’s GSH. No organ is more exposed to oxidants and foreign chemicals. So it makes biological sense to test GSH in NAFLD, non-alcoholic fatty liver disease.
Honda and colleagues ran a pilot study at several centers in Japan. It was open-label and had a single arm, so every patient got the treatment. The 34 patients had NAFLD proven by biopsy. They took 300 mg of oral GSH a day for four months [12]. The results:
- Alanine aminotransferase (ALT), a liver enzyme, fell by a significant amount from its starting level.
- Ferritin, triglycerides and non-esterified fatty acids also fell.
The authors said plainly that with no control arm, the study cannot show cause. They called for a randomized, placebo-controlled trial. No such follow-up has been published yet.
Other work has studied how GSH runs down in the liver in steatohepatitis, an inflamed fatty liver. Another line looks at the γ-glutamyl dipeptide metabolome, a set of small related molecules, as a biomarker for liver disease [11]. Both support the idea that GSH plays a part in liver disease. Neither amounts to a proven treatment.
Parkinson’s disease and the brain
The substantia nigra is a region of the brain. A loss of GSH there is one of the first chemical changes seen in Parkinson’s disease. It can be detected before movement symptoms show up [16]. For decades this has driven interest in replacing GSH to protect nerve cells.
- Sechi and colleagues, 1996. Nine patients with early, untreated Parkinson’s got 600 mg of IV GSH twice a day for 30 days. The study was open-label. Disability scores improved by 42% on average. The benefit held for two to four months once the doses stopped [3]. With no control group, firm conclusions are not possible.
- Hauser and colleagues, 2009. This later pilot trial was randomized, double-blind and placebo-controlled. It gave 21 Parkinson’s patients 1,400 mg of IV GSH three times a week for four weeks, or a placebo. The GSH group showed only a small trend toward better scores on the UPDRS, a Parkinson’s rating scale, and it was not significant. Most secondary endpoints showed no significant difference [5]. The authors concluded that patients tolerated the dose well, but it gave no benefit that mattered clinically.
Wider reviews of GSH in the brain raise a further problem. Two things make it hard to raise GSH in neurons with a dose given elsewhere in the body. One is the blood-brain barrier. The other is the way astrocytes, a kind of support cell, handle GSH. That holds for any route [16].
The current view among scientists who study neurodegeneration has three parts. GSH level is a valid biomarker. It is a reasonable target. But no supplement route has yet changed the course of disease in a trial large enough to tell.
Skin lightening
Glutathione is sold widely as a skin lightener, above all in parts of Asia. Products come as pills, creams and injections.
The reasoning goes like this. Melanin, the skin pigment, comes in a dark kind called eumelanin and a light kind called pheomelanin. GSH is thought to act on tyrosinase, an enzyme in the melanin pathway, and tilt production toward the light kind. The clinical support is limited and disputed.
- Weschawalit and colleagues, 2017. This randomized, placebo-controlled trial ran 12 weeks in 60 healthy middle-aged women. It tested oral GSH and oxidized GSSG at 250 mg a day. Against placebo, wrinkles, melanin index and skin elasticity improved by small amounts that were statistically significant. The absolute effects were modest. The trial did not establish whether they matter clinically [8].
- Sonthalia and colleagues, 2016 and 2018. These two systematic reviews looked at glutathione for skin whitening. They found the evidence too weak to support the claim. They found that injected GSH in particular does not have a good balance of benefit and risk. And they noted that several national regulators, the Philippines FDA among them, have issued warnings about injections [15], [17].
Unlicensed injections for skin lightening have been tied to reported side effects. They include Stevens-Johnson syndrome, severe abdominal pain, and thyroid, kidney and liver problems [17].
Skin lightening shows a pattern that runs through GSH research: strong basic chemistry, pushy sales claims, and a fairly thin clinical record.
Safety
- By mouth. In published trials, people mostly tolerated oral GSH well at doses as high as 1,000 mg a day for six months. No steady pattern of serious side effects was reported [9].
- By IV. Patients in the 2009 Hauser trial tolerated 1,400 mg, given three times a week for four weeks [5].
- Injections for skin lightening. Reports of serious side effects cluster around unlicensed injections for this use. They include Stevens-Johnson syndrome, severe abdominal pain, and thyroid, kidney and liver problems [17].
- Long-term use. No large, long-running safety data set exists for any ongoing supplement plan.
Legal status in the US
- No FDA approval as a treatment. As of April 2026, the FDA has not approved GSH for therapeutic use. Neither has the MHRA or the EMA. Specific IV products used in a few places for defined conditions are the exception.
- FDA warning. In 2019 the FDA warned about compounded IV GSH, citing sterility and compounding practices.
- Lab use. Research use of GSH in the laboratory is legal and routine. Biochemistry labs use it as a standard reagent.
Limits of the research
- Poor absorption by mouth. The gut breaks down most plain oral GSH. Studies of liposomal, under-the-tongue and long-term dosing show changes in biomarkers. They are still small and short.
- Weak clinical endpoints. Most trials report biomarkers such as plasma GSH, the GSSG ratio or markers of oxidative stress. They do not report outcomes that matter to patients. Two trials did use clinical endpoints, Hauser 2009 and Honda 2017. Their designs limit what can be said about cause.
- Missing comparisons. NAC and cysteine from whey protein cost less and are better understood as ways to raise GSH in cells. Few GSH trials test against an active alternative.
- Money shapes the record. The market for GSH, above all for skin-lightening injections, puts pressure on what gets published and promoted. Anyone weighing the evidence should take that into account [17].
- Route counts for more than dose. The question that matters in practice is “does this supplement raise GSH in the tissue I care about?” Studies seldom answer it directly. Plasma readings alone cannot be taken as the answer.
Glutathione’s job in the cell is settled science. Whether taking it changes anyone’s health is still an open question.
References
Peer-reviewed references, all PubMed-verified. Ordered by date of publication.
- Meister A, Anderson ME (1983). Glutathione. Annual Review of Biochemistry, 52, 711–760. PMID: 6137189
- Witschi A, Reddy S, Stofer B, Lauterburg BH (1992). The systemic availability of oral glutathione. European Journal of Clinical Pharmacology, 43(6), 667–669. PMID: 1362956
- Sechi G, Deledda MG, Bua G, et al. (1996). Reduced intravenous glutathione in the treatment of early Parkinson’s disease. Progress in Neuro-Psychopharmacology & Biological Psychiatry, 20(7), 1159–1170. PMID: 8938817
- Wu G, Fang YZ, Yang S, Lupton JR, Turner ND (2004). Glutathione metabolism and its implications for health. The Journal of Nutrition, 134(3), 489–492. PMID: 14988435
- Hauser RA, Lyons KE, McClain T, Carter S, Perlmutter D (2009). Randomized, double-blind, pilot evaluation of intravenous glutathione in Parkinson’s disease. Movement Disorders, 24(7), 979–983. PMID: 19230029
- Ballatori N, Krance SM, Notenboom S, Shi S, Tieu K, Hammond CL (2009). Glutathione dysregulation and the etiology and progression of human diseases. Biological Chemistry, 390(3), 191–214. PMID: 19166318
- Forman HJ, Zhang H, Rinna A (2009). Glutathione: overview of its protective roles, measurement, and biosynthesis. Molecular Aspects of Medicine, 30(1–2), 1–12. PMID: 18796312
- Weschawalit S, Thongthip S, Phutrakool P, Asawanonda P (2017). Glutathione and its antiaging and antimelanogenic effects. Clinical, Cosmetic and Investigational Dermatology, 10, 147–153. PMID: 28490897
- Richie JP Jr, Nichenametla S, Neidig W, et al. (2015). Randomized controlled trial of oral glutathione supplementation on body stores of glutathione. European Journal of Nutrition, 54(2), 251–263. PMID: 24791752
- Schmitt B, Vicenzi M, Garrel C, Denis FM (2015). Effects of N-acetylcysteine, oral glutathione (GSH) and a novel sublingual form of GSH on oxidative stress markers: A comparative crossover study. Redox Biology, 6, 198–205. PMID: 26262996
- Soga T, Sugimoto M, Honma M, et al. (2011). Serum metabolomics reveals γ-glutamyl dipeptides as biomarkers for discrimination among different forms of liver disease. Journal of Hepatology, 55(4), 896–905. PMID: 21334394
- Honda Y, Kessoku T, Sumida Y, et al. (2017). Efficacy of glutathione for the treatment of nonalcoholic fatty liver disease: an open-label, single-arm, multicenter, pilot study. BMC Gastroenterology, 17(1), 96. PMID: 28789631
- Sinha R, Sinha I, Calcagnotto A, et al. (2018). Oral supplementation with liposomal glutathione elevates body stores of glutathione and markers of immune function. European Journal of Clinical Nutrition, 72(1), 105–111. PMID: 28853742
- Lapenna D, Ciofani G, Calafiore AM, Cipollone F, Porreca E (2018). Impaired glutathione-related antioxidant defenses in the arterial tissue of diabetic patients. Free Radical Biology & Medicine, 124, 525–531. PMID: 29964170
- Sonthalia S, Daulatabad D, Sarkar R (2016). Glutathione as a skin whitening agent: Facts, myths, evidence and controversies. Indian Journal of Dermatology, Venereology and Leprology, 82(3), 262–272. PMID: 27088927
- Aoyama K (2021). Glutathione in the Brain. International Journal of Molecular Sciences, 22(9), 5010. PMID: 34065042
- Sonthalia S, Jha AK, Lallas A, Jain G, Jakhar D (2018). Glutathione for skin lightening: a regnant myth or evidence-based verity? Dermatology Practical & Conceptual, 8(1), 15–21. PMID: 29445569
- Minich DM, Brown BI (2019). A Review of Dietary (Phyto)Nutrients for Glutathione Support. Nutrients, 11(9), 2073. PMID: 31484368
- Kern JK, Geier DA, Adams JB, Garver CR, Audhya T, Geier MR (2011). A clinical trial of glutathione supplementation in autism spectrum disorders. Medical Science Monitor, 17(12), CR677–682. PMID: 22129897
Related compounds
- NAD+: Helper molecule in every cell, studied for energy, DNA repair and its drop with age.
- GHK-Cu: Copper-bound chain of three amino acids, tested in cells and animals for skin and wound repair.
- Thymosin Alpha-1: Immune peptide from the thymus, sold as an approved drug in many countries.