PT-141, also called bremelanotide, is a lab-made peptide that acts on the brain. The FDA approved it in 2019 as Vyleesi for low sexual desire in women who have not reached menopause. That is its only approved use.
In brief
- It raises sexual arousal through melanocortin receptors in the brain, not by widening blood vessels, so it works differently from PDE5 inhibitors.
- It grew out of Melanotan 2 research and was picked because it acts mainly in the brain and darkens skin less.
- The FDA approved it in 2019 as Vyleesi for hypoactive sexual desire disorder in women before menopause, and for nothing else.
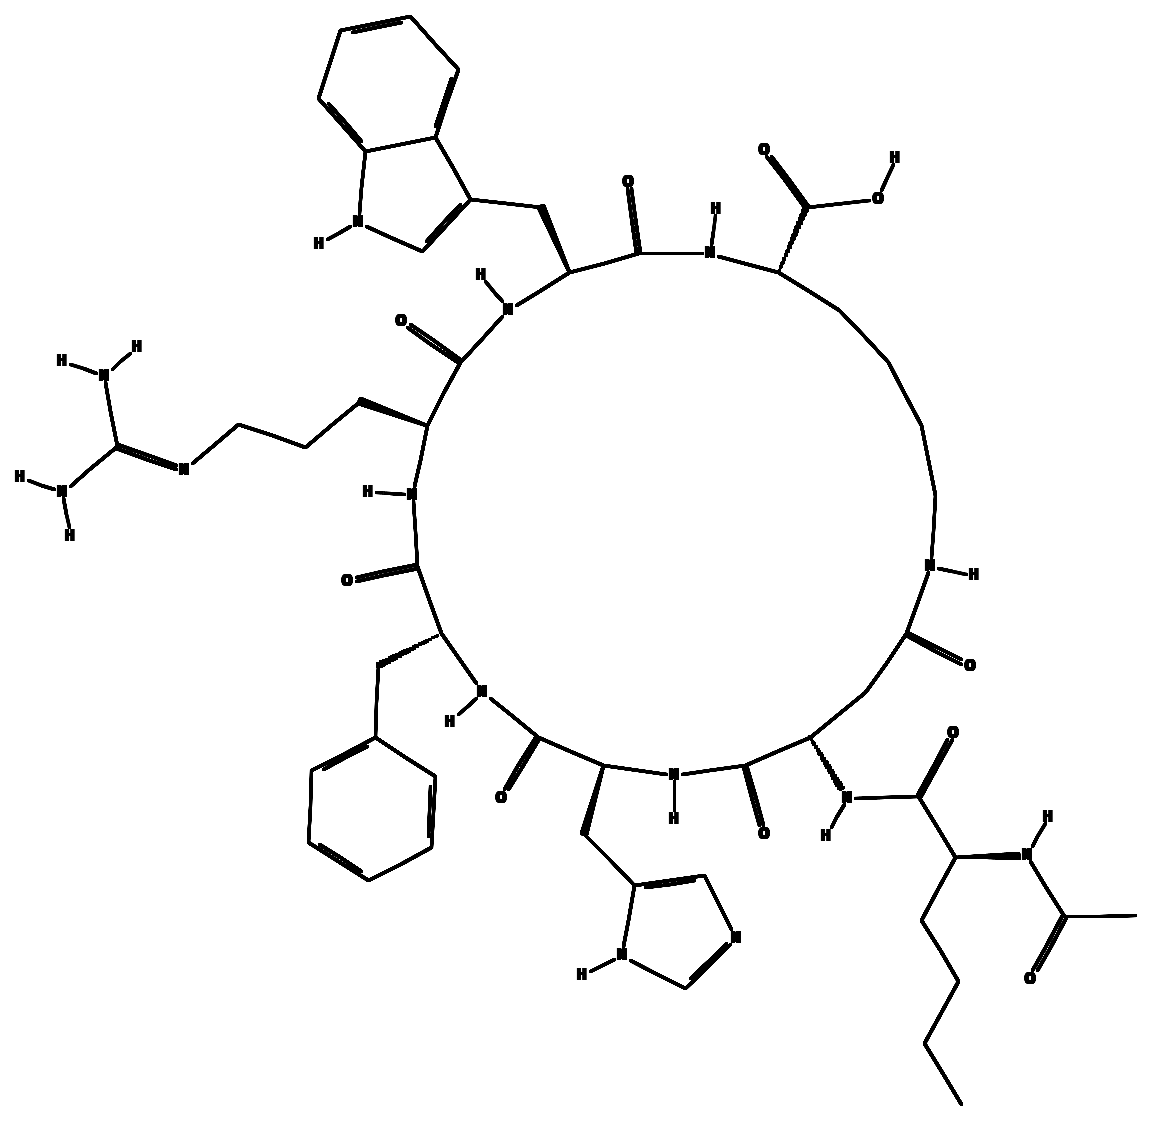
What PT-141 is
PT-141 is a lab-made peptide that has been through full human trials. Two Phase 3 trials tested it in 1,247 women [2]. In June 2019 the FDA approved it for one use: hypoactive sexual desire disorder (HSDD) in women who have not reached menopause [1]. HSDD is low sexual desire that causes distress. The drug name is bremelanotide. It is sold as Vyleesi, a 1.75 mg shot under the skin from an autoinjector pen [1].
Regulators in Europe and the UK, the EMA and the MHRA, have not cleared it. The European application was pulled in 2019 [1].
A peptide is a short chain of amino acids, the building blocks of protein. PT-141 is a ring of seven. It is an agonist, which means it switches receptors on. Its targets are the melanocortin receptors, a family of switches on cells. It can turn on any of them, but it favors two called MC3R and MC4R over a third called MC1R [9][11].
Where it came from
PT-141 was built from an older compound, Melanotan II (MT-II). The Hadley and Hruby group at the University of Arizona made MT-II as a longer-lasting version of a natural hormone, α-melanocyte-stimulating hormone (α-MSH) [11][15].
A company called Palatin Technologies then picked PT-141 from a set of MT-II variants. The aim was to keep the brain signal that raises sexual interest and cut the skin-darkening effect tied to MC1R [9].
Drugs like sildenafil, known as PDE5 inhibitors, work on blood vessels in the penis. PT-141 is different. It works in the brain, on melanocortin circuits in the hypothalamus that are linked to sexual drive and arousal [4][13].
How much research there is
There are large human trials for one use in women, smaller and older trials in men, and animal and receptor studies behind both. The grades use the system for this whole site. “Approved pharma derivative” covers the one FDA-approved use and nothing else.
| Area | Main studies | What was tested | Evidence grade |
|---|---|---|---|
| HSDD in women before menopause | Kingsberg 2019, RECONNECT 301 and 302 [2]. Clayton 2016, Phase 2 [8] | Phase 2 and Phase 3 randomized trials, about 1,644 women in all | Approved pharma derivative (FDA only) |
| Long-term safety in HSDD | Simon 2019 [3] | A 52-week extension in which everyone knew they were getting the drug | Clinical (moderate) |
| Erection problems in men (older work) | Diamond 2004 [5]. Rosen 2004 [6]. Safarinejad 2008 [7] | Phase 1 and 2 randomized trials, by nasal spray and by shot under the skin | Early clinical (program stopped) |
| Sexual behavior and the brain | Pfaus 2004 [4]. Kingsberg 2015 review [13] | Female rats, plus a review of how it works | Preclinical |
| How it acts on melanocortin receptors | Molinoff 2003 [9]. Hadley 2006 [11]. King 2007 [15]. Shadiack 2007 [10] | Receptor binding tests, studies of structure and activity, and a history review | Mechanistic |
How it works
Scientists have mapped how PT-141 acts using receptor binding tests, animal behavior studies and human drug studies. Its effect on sex drive seems to start in the brain, not in the blood vessels.
Which receptors it turns on
There are five melanocortin receptors, MC1R through MC5R. PT-141 can switch on all of them. It is stronger at MC3R and MC4R, and weaker at MC1R than its parent MT-II [9][11].
- MC4R is packed into parts of the hypothalamus that control appetite, sexual behavior and the body’s automatic functions [15].
- MC3R has a part in energy balance and in the brain circuits behind motivated behavior [15].
- MC1R is tied to skin pigment. The designers wanted less action here so the skin would darken less. Some skin darkening has still been reported in patients [3].
It acts in the brain
Rodent studies traced the effect to the hypothalamus. Two spots there are thought to be involved, the medial preoptic area and the paraventricular nucleus [4][13].
Pfaus and colleagues gave a melanocortin agonist to female rats. The rats showed more mating invitation behaviors, called solicitations and hops and darts. They did not just move around more. That points to an effect on sexual drive itself, not on general alertness [4].
Reviews of the female sexual response place melanocortin signals in the brain next to two other pathways, dopamine and noradrenaline. All three feed the desire stage of that response [13].
How it differs from PDE5 inhibitors
Sildenafil and other PDE5 inhibitors act in the body, not the brain. They boost the effect of nitric oxide, which relaxes smooth muscle in the erectile tissue of the penis. For that to produce an erection, arousal in the brain must already be working [7].
PT-141 has been tested in patients who got no result from PDE5 inhibitors. That supports the idea that it acts at a different, earlier step in the sexual response [7]. The approved use fits this picture. HSDD is a problem of desire, not of blood flow [1][2].
How the body handles it
Early human studies used a nasal spray or a drip into a vein. The approved product is a 1.75 mg dose under the skin from a single-use autoinjector. The label says it is taken as needed, at least 45 minutes before expected sexual activity [1].
After a shot under the skin, blood levels peak within about one hour. The half-life, the time for half the dose to clear, is around two to three hours. This pattern suits use as needed, not steady daily use [1][6]. The label caps use at one dose in 24 hours and eight doses per month [1].
What the studies found
The research covers three areas: receptor and animal work, older trials in men that have since been dropped, and the Phase 3 RECONNECT trials behind the US approval.
The RECONNECT trials
The main evidence comes from two Phase 3 trials with the same design, RECONNECT Study 301 and Study 302. Kingsberg and colleagues reported them in Obstetrics & Gynecology in 2019 [2].
- Who: 1,247 women with HSDD who had not reached menopause, across the two trials.
- What they got: half were assigned by chance to bremelanotide 1.75 mg and half to a placebo. They gave themselves the shot under the skin as needed for 24 weeks.
- What was measured: two main goals. One was the change in the desire score of the Female Sexual Function Index (FSFI-D). The other was the change in the distress score on item 13 of the Female Sexual Distress Scale-DAO [2].
- Result: both trials hit both goals. Desire went up and distress went down compared with placebo, and the gaps were statistically significant [2].
The size of the effect was modest in absolute terms. Authors who write about HSDD are still debating how much the changes mean for patients [14].
Earlier work in women
The HSDD program grew out of the rat data from Pfaus, which showed a pro-sexual effect of melanocortin agonists that was specific to females [4].
Next came a Phase 2 study by Clayton and colleagues, with 397 women. It enrolled women before menopause who had HSDD or female sexual arousal disorder. It tested three doses under the skin: 0.75, 1.25 and 1.75 mg. The results showed that response rose with dose. They also shaped the RECONNECT design, and the 1.75 mg dose was picked to go forward into Phase 3 [8].
Across the Phase 2 and Phase 3 data, bremelanotide gave steady but modest gains. Women reported more desire and less distress about low desire [2][8][14].
Only two drugs are approved in the US specifically for HSDD before menopause. The other is flibanserin. Reviews note that the two work differently. Bremelanotide turns on melanocortin receptors in the brain, and flibanserin has mixed effects on serotonin [13][14].
Older trials in men
PT-141 was first developed as a nasal spray for erection problems in men.
- Diamond and colleagues ran a double-blind, placebo-controlled study. It enrolled men with erectile dysfunction (ED) as well as healthy men. They used RigiScan to measure rigidity. Rigidity of the penis rose with the dose of the nasal spray [5].
- Rosen and colleagues followed with a shot under the skin. They tested healthy men and also men who had not responded to sildenafil. They also saw erections they could measure [6].
- Safarinejad later published a randomized study, run in a clinic, of bremelanotide under the skin in men whose ED had not responded to sildenafil [7].
The nasal spray program for men ended in 2008. The FDA had raised concerns that the spray pushed blood pressure up as the dose went up. After that, work shifted to dosing under the skin and to HSDD in women [1].
Safety
Simon and colleagues reported the long-term safety results. They pooled the main RECONNECT studies with a 52-week extension in which all the women knew they were on the drug [3].
Common side effects
- Nausea was the most common. About 40% of women on bremelanotide had it, against 1% on placebo. It caused most of the dropouts [3].
- Flushing, reactions where the shot went in, and headache were also among the most common [3].
Blood pressure and heart rate
In the hours after a dose, blood pressure rose for a short time. The top number went up by about 2.8 mmHg, and the bottom number rose too. Heart rate went down. The label rules out use in women with high blood pressure that is not under control or with known heart and blood vessel disease. It also calls for blood pressure to be under control before starting and to be checked during use [1][3].
This effect comes with turning on melanocortin receptors in general. It is not special to the approved product.
Skin darkening
A minority of women got dark patches on the face, gums and breasts. It happened more often with repeated doses. It faded partly after they stopped the drug [3].
Legal status in the US
- FDA approved for one use. The FDA approved bremelanotide on June 21, 2019, under the brand name Vyleesi. The approval covers acquired, generalized HSDD in women before menopause, given by autoinjector under the skin [1].
- No other approvals. The application to the EMA was withdrawn in 2019 before any decision, and the MHRA has not approved it. Nothing in Europe matches the US approval [1].
- Other uses are not approved anywhere. That includes use in women after menopause, sexual problems in men, tanning, and the general “sexual performance” uses seen in the gray market [1][14].
- Sport. The World Anti-Doping Agency did not list bremelanotide as banned on its 2025 Prohibited List. That status can change from year to year, and single sports may have their own rules.
- Research use. PT-141 sold for research is supplied for laboratory use only.
Limits of the research
- One narrow approval. The only use any regulator has approved is Vyleesi for acquired, generalized HSDD in women before menopause [1]. No regulator backs any wider use.
- A modest effect. In RECONNECT, the gains in desire and the drops in distress were statistically significant but small in absolute terms. Whether they matter to patients is debated [2][14]. The evidence does not show a high-powered treatment.
- Nausea is common. About 40% of treated women in the main trials reported it, and it was the top reason for quitting [3].
- A blood pressure signal. The short rise in blood pressure comes with this class of compound, and the label bars some patients because of it [1][3].
- The male program was dropped. The trials in men were early stage, and the nasal spray work ended in 2008.
PT-141 has Phase 3 trials and an FDA approval behind it, but the approval covers one group of patients and the benefit was modest.
References
Selected peer-reviewed references. Not exhaustive. DOI or PubMed identifiers are provided for each source.
- Dhillon S, Keam SJ (2019). Bremelanotide: First Approval. Drugs, 79(14), 1599–1606. DOI
- Kingsberg SA, Clayton AH, Portman D, Williams LA, Krop J, Jordan R, Lucas J, Simon JA (2019). Bremelanotide for the Treatment of Hypoactive Sexual Desire Disorder: Two Randomized Phase 3 Trials. Obstetrics & Gynecology, 134(5), 899–908. DOI
- Simon JA, Kingsberg SA, Portman D, Williams LA, Krop J, Jordan R, Lucas J, Clayton AH (2019). Long-Term Safety and Efficacy of Bremelanotide for Hypoactive Sexual Desire Disorder. Obstetrics & Gynecology, 134(5), 909–917. DOI
- Pfaus JG, Shadiack A, Van Soest T, Tse M, Molinoff P (2004). Selective facilitation of sexual solicitation in the female rat by a melanocortin receptor agonist. Proceedings of the National Academy of Sciences USA, 101(27), 10201–10204. DOI
- Diamond LE, Earle DC, Rosen RC, Willett MS, Molinoff PB (2004). Double-blind, placebo-controlled evaluation of the safety, pharmacokinetic properties and pharmacodynamic effects of intranasal PT-141, a melanocortin receptor agonist, in healthy males and patients with mild-to-moderate erectile dysfunction. International Journal of Impotence Research, 16(1), 51–59. DOI
- Rosen RC, Diamond LE, Earle DC, Shadiack AM, Molinoff PB (2004). Evaluation of the safety, pharmacokinetics and pharmacodynamic effects of subcutaneously administered PT-141, a melanocortin receptor agonist, in healthy male subjects and in patients with an inadequate response to Viagra. International Journal of Impotence Research, 16(2), 135–142. DOI
- Safarinejad MR, Hosseini SY (2008). Salvage of sildenafil failures with bremelanotide: a randomized, double-blind, placebo controlled study. Journal of Urology, 179(3), 1066–1071. DOI
- Clayton AH, Althof SE, Kingsberg S, DeRogatis LR, Kroll R, Goldstein I, Kaminetsky J, Spana C, Lucas J, Jordan R, Portman DJ (2016). Bremelanotide for female sexual dysfunctions in premenopausal women: a randomized, placebo-controlled dose-finding trial. Women’s Health (London), 12(3), 325–337. DOI
- Molinoff PB, Shadiack AM, Earle D, Diamond LE, Quon CY (2003). PT-141: a melanocortin agonist for the treatment of sexual dysfunction. Annals of the New York Academy of Sciences, 994, 96–102. DOI
- Shadiack AM, Sharma SD, Earle DC, Spana C, Hallam TJ (2007). Melanocortins in the treatment of male and female sexual dysfunction. Current Topics in Medicinal Chemistry, 7(11), 1137–1144. DOI
- Hadley ME, Dorr RT (2006). Melanocortin peptide therapeutics: historical milestones, clinical studies and commercialization. Peptides, 27(4), 921–930. DOI
- Wessells H, Gralnek D, Dorr R, Hruby VJ, Hadley ME, Levine N (2000). Effect of an alpha-melanocyte stimulating hormone analogue on penile erection and sexual desire in men with organic erectile dysfunction. Urology, 56(4), 641–646. DOI
- Kingsberg SA, Clayton AH, Pfaus JG (2015). The Female Sexual Response: Current Models, Neurobiological Underpinnings and Agents Currently Approved or Under Investigation for the Treatment of Hypoactive Sexual Desire Disorder. CNS Drugs, 29(11), 915–933. DOI
- Edinoff AN, Sanders NM, Lewis KB, Apgar TL, Cornett EM, Kaye AM, Kaye AD (2022). Bremelanotide for Treatment of Female Hypoactive Sexual Desire. Neurology International, 14(1), 75–88. DOI
- King SH, Mayorov AV, Balse-Srinivasan P, Hruby VJ, Vanderah TW, Wessells H (2007). Melanocortin Receptors, Melanotropic Peptides and Penile Erection. Current Topics in Medicinal Chemistry, 7(11), 1098–1106. DOI
Related compounds
- Melanotan 2: Lab-made copy of a skin-darkening hormone. Never approved, with reports of harm in users.
- Kisspeptin: Brain signal that starts the puberty and fertility hormone chain, tested in small human trials.
- BPC-157: Lab-made chain of 15 amino acids, tested in animals for blood vessel growth and tissue repair.